Shoulder pain that stops you reaching a seatbelt, fastening a bra strap or sleeping on one side is usually blamed on a frozen shoulder or a torn rotator cuff. The two get confused constantly, because both hurt most at night and both make lifting the arm difficult.
They are different problems, and the difference shows in one thing: whether the shoulder can still be moved by someone else. Knowing that distinction helps you describe your symptoms accurately and makes the assessment quicker.
What the rotator cuff does
Four small muscles run from the shoulder blade and wrap around the top of the arm bone as tendons. They hold the ball of the shoulder centred in a shallow socket while larger muscles do the lifting, and they rotate the arm in and out.
When one of those tendons tears, the shoulder loses power rather than movement. Tears happen gradually, as tendons weaken with age, or suddenly, after a fall, a heavy lift or catching something falling.
Two different patterns
Frozen shoulder
The capsule surrounding the joint thickens and contracts, so the joint cannot move through its full range. Range is lost whether you move the arm yourself or someone else moves it for you. Turning the forearm outwards with the elbow tucked at your side is usually the first movement to go.
It runs in three overlapping phases: a painful freezing phase, a frozen phase where pain eases but stiffness dominates, and a slow thawing phase as movement returns. The whole process commonly takes many months to a couple of years. It is most common between 40 and 60 and in women, and appears more often with diabetes or thyroid conditions, and after the arm has been rested, injured or operated on.
Rotator cuff tear
Here the problem is power. Lifting the arm out to the side is weak, holding a full cup at arm’s length is hard, and the arm may drop if you lower it slowly from above shoulder height. Many people compensate with a shrug to get the arm up.
Passive movement is usually preserved: if someone lifts your relaxed arm, it goes most of the way. Night pain lying on that side is common, as is pain reaching behind the back. Gradual tears are common after 50, while a sudden tear follows a specific incident.
Other causes worth ruling out
- Subacromial impingement and bursitis: pain through the middle of the lifting arc, with range and power largely intact.
- Calcific tendinitis: a calcium deposit in a tendon causing intense pain that starts abruptly and lasts days, usually visible on an X-ray.
- Shoulder arthritis: gradual stiffness in all directions with grinding, which can look very like a frozen shoulder until an X-ray is taken.
- Referred pain from the neck: pain past the elbow, sometimes with tingling, that changes with neck position rather than shoulder movement.
How the difference is confirmed
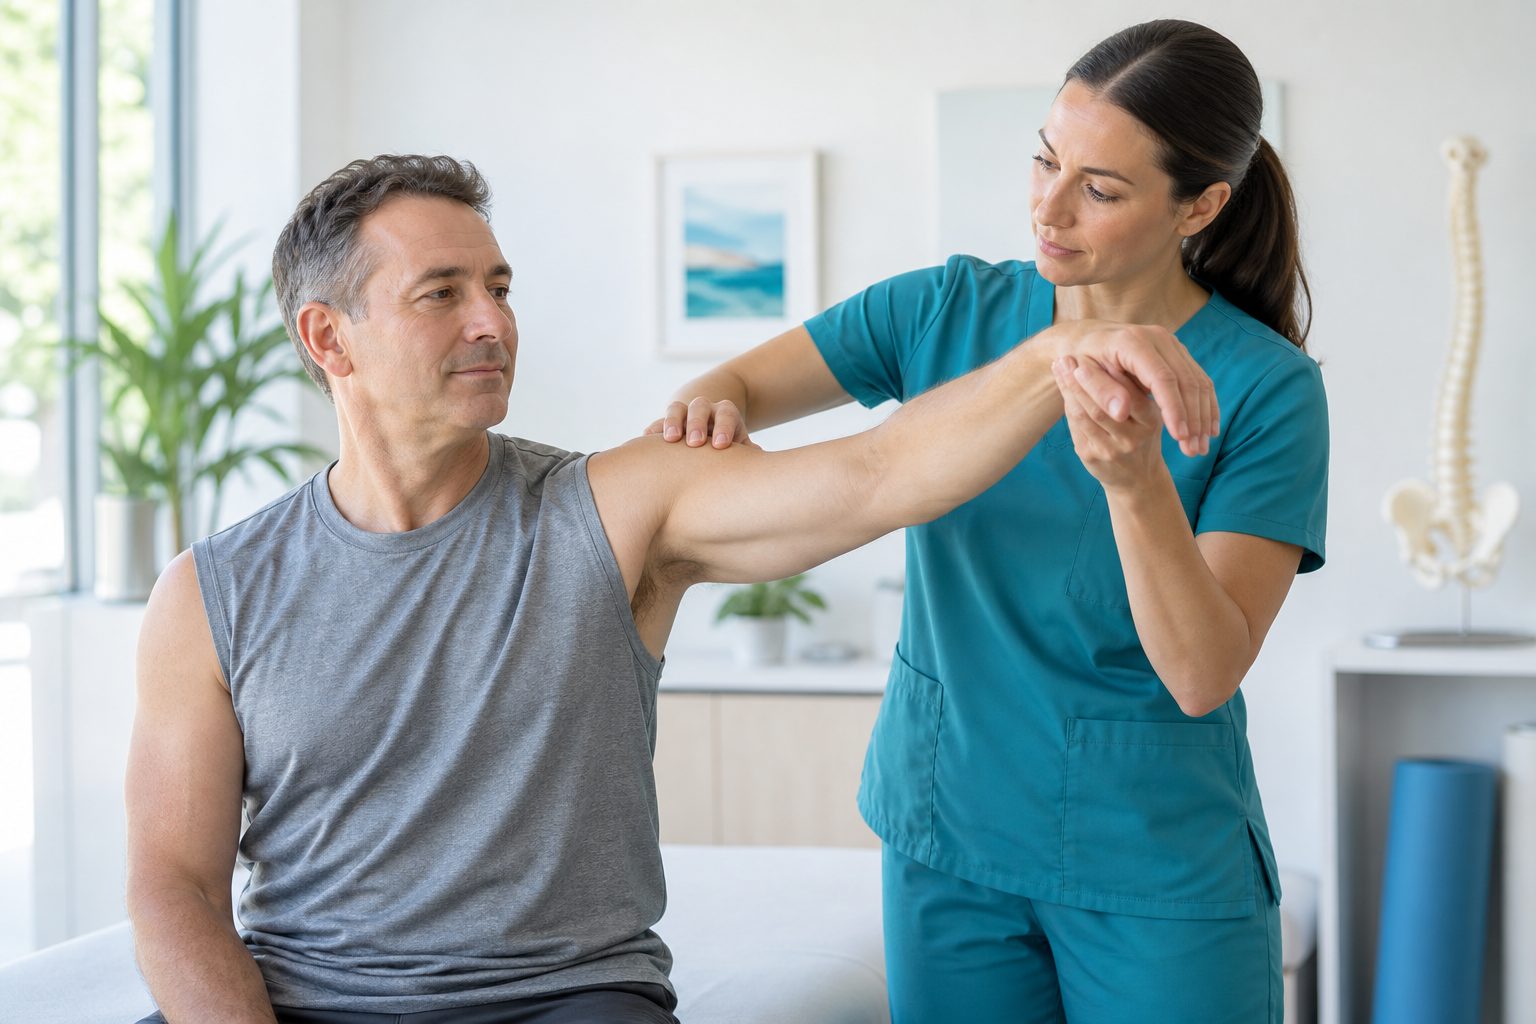
Examination does most of the work. The specialist compares what you can do actively with what the shoulder allows passively, then tests each tendon against resistance: the empty can test for the tendon on top of the shoulder, and pressing the palm into the belly for the one at the front.
Imaging is chosen to answer a question, not used routinely. An X-ray shows arthritis, calcium deposits and the position of the ball in the socket. Ultrasound is quick, lets the tendon be watched while the arm moves, and shows cuff tears well. MRI gives the fullest picture of tendon and muscle quality, and is used mainly when surgery is being planned or the diagnosis is unclear.

Treatment paths for each
Frozen shoulder
Most cases are carried by time and a structured physiotherapy programme, working within tolerable range rather than forcing through pain. Controlling pain early matters, because a guarded shoulder stiffens further. A guided injection into the joint can reduce pain enough for rehabilitation to progress, and an injection of fluid to stretch the capsule is sometimes used. Surgery to release the capsule is kept for shoulders still stiff after many months of genuine treatment.
Rotator cuff tear
Many gradual tears do well without surgery. Strengthening the remaining cuff and the surrounding muscles can restore useful function, and pain relief or an injection may support that work. Repair is considered for a sudden tear in an active person, for significant weakness, and for tears still causing pain and loss of function after months of rehabilitation. It is usually done with keyhole surgery, followed by a sling and a staged programme over several months. A sudden tear after an injury in an active person should be assessed within a few weeks rather than after months of rehabilitation, because repair options narrow with time.
Warning signs that need prompt assessment
Arrange urgent review if you have:
- Inability to lift the arm at all after a fall, a dislocation or a direct blow.
- Sudden loss of power in the arm, especially with a tearing sensation at the time of injury.
- Fever with a hot, swollen, red shoulder, which can mean infection in the joint.
- Visible deformity after an injury, or the arm held fixed in one position.
- Numbness, pins and needles or coldness in the hand after a shoulder injury.
Frequently asked questions
What should I notice before my appointment?
Notice whether the shoulder stays stiff even when the arm is relaxed and someone else moves it gently, or whether it moves freely but cannot be lifted or held up. Notice whether the pain is worse at night on that side, and whether there was a specific injury. Bring those observations to the consultation. The distinction is confirmed on examination, not at home.
How long does a frozen shoulder take to recover?
It is slow. Many people take a year or more from first symptoms to comfortable movement, and the stiff middle phase can feel like no progress at all. Consistent gentle work and good pain control make the worst phase more bearable and protect the movement you still have.
Does a rotator cuff tear always need surgery?
No. Many partial and gradual tears are managed well with rehabilitation. Surgery is discussed for a sudden tear in an active arm, marked weakness, or ongoing pain and limitation after a proper trial of physiotherapy.
Can I keep going to the gym with shoulder pain?
Usually yes, with changes. Overhead pressing, upright rows and heavy dips aggravate both problems, while controlled rotation work, rowing at chest height and lower body training generally continue.
Getting it assessed
Shoulders reward an accurate diagnosis, because treatment for stiffness and treatment for weakness pull in different directions. If your shoulder has been painful for more than a few weeks, wakes you at night, or is losing power, an examination usually gives the answer in one visit. Our shoulder specialists consult at hospitals across Bali, and you can book a consultation or message the clinic on WhatsApp.
This article is general information, not medical advice. Any persistent or severe symptom should be assessed by a qualified orthopaedic specialist in person.